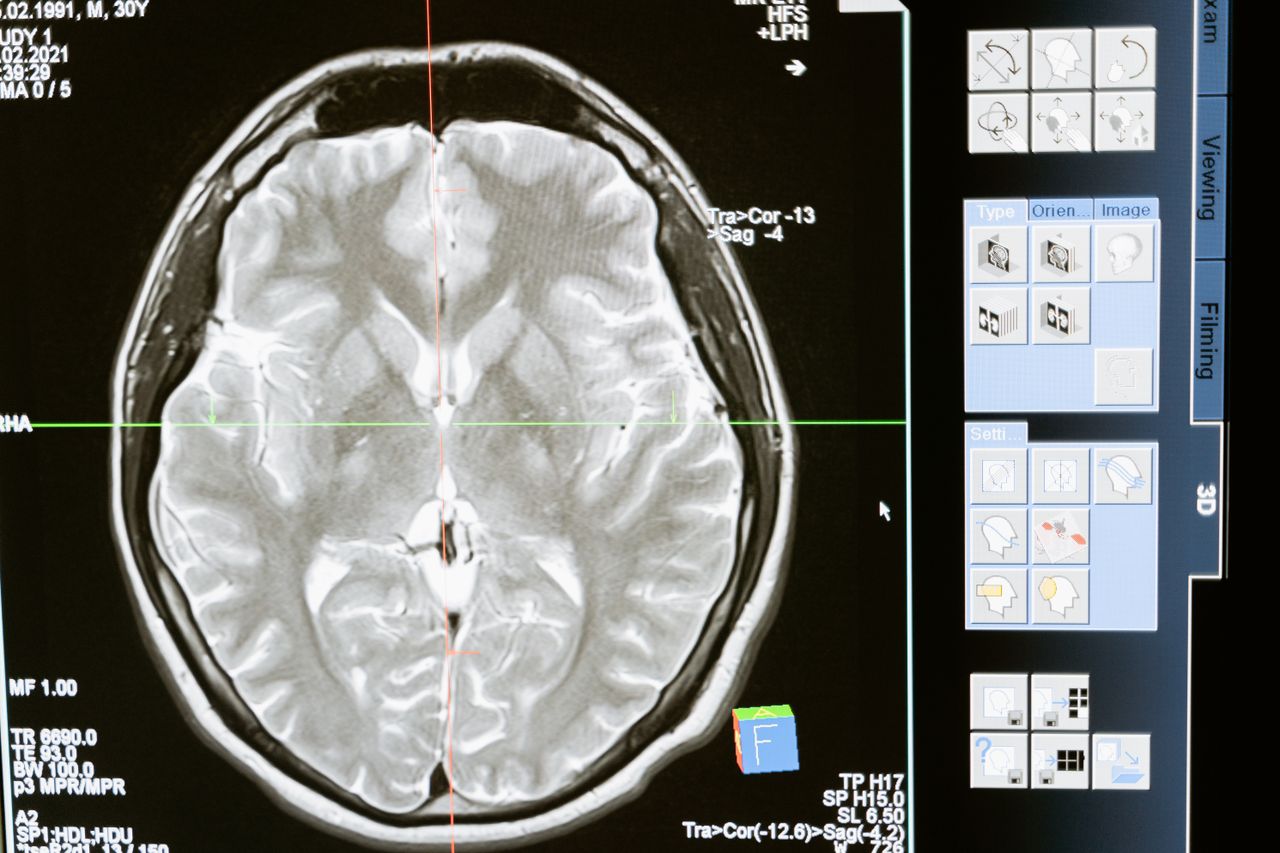
AI tools that detect ARIA on brain MRI in patients receiving anti-amyloid therapy for Alzheimer disease now have enough evidence behind them for clinical use, as long as the radiologist keeps ownership of the report. That is the conclusion of a multidisciplinary panel of neuroradiologists and Alzheimer disease clinicians, published September 16 in the American Journal of Roentgenology (AJR). The group recommends conditional implementation: AI as clinical decision support, with the specialist validating every finding in what the authors call a radiologist-in-the-loop framework.
Who wrote it and what the panel recommends
The paper, an expert opinion article (DOI 10.2214/AJR.26.35514), brings together leading names in dementia neuroimaging: Jeffrey Petrella and P. Murali Doraiswamy (Duke), Frederik Barkhof (UCL and Amsterdam UMC), Tammie Benzinger (Mallinckrodt Institute, Washington University), Petrice Cogswell (Mayo Clinic), Ana Franceschi (Northwell), Marwan Sabbagh (Barrow Neurological Institute), Stephen Salloway (Brown) and Greg Zaharchuk (Stanford). They reviewed how much evidence exists to move these systems into routine practice, how to integrate them safely, and what remains unknown.
The key points, based on the paper’s abstract and ITN’s coverage:
Higher sensitivity. Reader performance studies show that AI assistance raises sensitivity by roughly 16 percentage points for ARIA-E and 10 points for ARIA-H, while reducing interreader variability. Slightly lower specificity. The drop ranges from 3 to 9 percentage points; the panel judged that avoiding missed or delayed ARIA outweighs the extra work of reviewing false positives. Radiologist accountability. The final read belongs to the physician, who must check AI output against the full examination and clinical context. Heterogeneous products. The commercial tools named — icometrix icobrain aria, cortechs.ai NeuroQuant Lesion Surveillance, Neurophet AQUA AD Plus and Qynapse QyScore — differ substantially in FDA clearance status, technical capabilities and validation evidence. Safeguards. Standardized acquisition protocols, local validation, radiologist training, ongoing quality audits and participation in real-world registries such as ALZ-NET and InRAD.
Where the 16 and 10 points come from
The figures match the largest reader study published on the topic so far: Sima and colleagues in JAMA Network Open (2024), a study run by icometrix with Biogen. Sixteen board-certified radiologists read 199 retrospective cases — each a baseline and a post-dosing MRI from the aducanumab trials PRIME, EMERGE and ENGAGE — with and without icobrain aria. Sensitivity rose from 71% to 87% for ARIA-E and from 69% to 79% for ARIA-H, while specificity stayed above 80% for both. Assisted area under the curve was 0.87 for ARIA-E and 0.83 for ARIA-H.
The design matters: trial cases with relatively controlled acquisition protocols, and only 2 of the 16 readers were neuroradiologists. The gain tends to be largest for readers who do not see ARIA every day — which is both the argument for the tool and a limit on extrapolating the result to specialized centers.
Why ARIA is a volume problem
Lecanemab and donanemab, monoclonal antibodies against amyloid beta, slow cognitive decline in early Alzheimer disease to a clinically meaningful degree. The trade-off is ARIA in two forms. ARIA-E is vasogenic edema or sulcal effusion, seen as FLAIR hyperintensity. ARIA-H covers microhemorrhages and superficial siderosis, identified on susceptibility-weighted sequences (T2* GRE or SWI). Most episodes are asymptomatic and occur in the first months of treatment, with higher risk in APOE ε4 homozygotes.
That is why the drug labels require a baseline MRI and scheduled surveillance MRIs before specific early infusions, plus imaging whenever symptoms appear. Radiographic severity — defined by the extent of edema or the microhemorrhage count — drives the decision to pause, resume or stop therapy. This is a comparative read with direct therapeutic consequences, not an incidental finding.
The panel estimated that if 10% of U.S. patients with mild cognitive impairment or early Alzheimer dementia are treated, monitoring would generate 7 to 8 million additional MRI exams. That volume, combined with how subtle punctate microhemorrhages and small sulcal effusions can be, is the classic recipe for fatigue, interreader variability and missed findings — exactly where detection and longitudinal quantification algorithms tend to pay off.
What changes for imaging departments
The recommendation is not simply “buy software.” The panel sets preconditions that depend on each site. First, protocol: without standardized FLAIR and susceptibility sequences between baseline and follow-up, no algorithm compares well — and neither does the radiologist. Second, local validation, because performance on clinical trial data does not guarantee performance on a given site’s scanner fleet. Third, auditing: tracking agreement between AI and final report, false-positive rates and missed cases over time.
The move tracks the regulatory trend. Radiology accounts for most AI-enabled devices authorized by the FDA, as we reported in Radiology Holds 76% of FDA AI Authorizations. Dementia neuroimaging is also going through a biomarker expansion, from the FDA approval of Lantheus’ tau PET agent to MRI techniques such as MR-AIV, which maps brain fluid flow with AI.
For Brazil and Latin America, the discussion is timely. With donanemab registered by Brazil’s regulator Anvisa in 2025, centers starting to treat patients will need a reliable surveillance MRI workflow, often outside dedicated neuroradiology centers. That is precisely the setting where AI assistance showed the largest sensitivity gain. Local availability of these tools, their regulatory status and their validation on regional scanners and protocols still need to be checked case by case.
Limitations and what remains to be proven
The panel itself acknowledges the gaps. Current evidence measures reading accuracy, not clinical outcomes: it is still unknown whether detecting more mild, asymptomatic ARIA changes patient trajectories or simply increases dose suspensions. Reader studies come mostly from trial data, often manufacturer-funded, and from aducanumab rather than the antibodies now in use. The loss of specificity, small in percentage terms, can add up at scale: across millions of exams, a few points mean a lot of alerts to review.
That is why the paper calls for prospective studies on outcomes and long-term care, and for feeding registries such as ALZ-NET. “AI-assisted ARIA detection is likely to enhance patient safety when used as clinical decision support within a radiologist-in-the-loop framework,” the authors conclude. Until outcome data arrive, the recommendation is pragmatic: use it, but measure it.
Source: ITN (Imaging Technology News)